

 Rebecca Yee, MD

Progesterone is a hormone that’s commonly used alongside estrogen to treat menopause symptoms, including vasomotor symptoms, brain fog, and sleep disturbance. Low-dose progesterone is an essential part of hormone therapy for women with a uterus; it helps balance estrogen’s effects and helps reduce the risk of uterine cancer. Here, we’ll answer your questions about progesterone dosage for menopause. At Midi Health, we typically start with 100 milligrams (mg) daily, but dosing is always tailored to your unique needs.
If there’s one thing we know about menopause, it’s that you want to put an end to persistent, frustrating symptoms—and fast. We get how critical it is to find treatments that can make a real difference in how you feel and, quite frankly, help you get your life back. You no longer want to erupt in sweat as a hot flash washes over you in the middle of the workday. You don’t want to feel as irritated as you do about, well, everything. You don’t want constant headaches to disrupt your plans with friends. You’re ready for a decent night’s sleep.
So, if your clinician told you that your symptoms were likely related to menopause, it may have been a relief knowing that treatment—hormone replacement therapy (HRT, now commonly referred to as menopause hormone therapy, or MHT), in particular—could help you feel a lot more like you again.
Progesterone is a hormone often used in HRT alongside estrogen. And it’s completely understandable to have questions about it: what it is, what it does, and how much of it you actually need. At Midi, we often hear from women who have questions about progesterone dosage for menopause, including whether they should take the lowest dose of progesterone for HRT.
That question often stems from outdated 2002 data about HRT that linked taking estrogen plus progesterone to an increased risk of breast cancer and heart disease. But the study in question was widely misinterpreted and the risks exaggerated, says certified menopause practitioner Lauren Streicher, MD, a clinical professor of obstetrics and gynecology at Northwestern University’s Feinberg School of Medicine and the founding medical director of the Northwestern Medicine Center for Sexual Medicine and Menopause.
"Some women are aware that in that old study from 2002, it was not the estrogen that caused the increased risk of breast cancer—it was the progesterone," explains Dr. Streicher. "And the progesterone that was used then was not a natural progesterone, it was a synthetic one.” Today, oral micronized progesterone—which is chemically identical to the kind your body makes—is most often recommended for HRT and appears to be associated with lower breast cancer risks than synthetic progestins. Even so, that outdated study is still one of the reasons why some women want to take the lowest dose progesterone possible. "It’s important to realize that’s not necessary," Dr. Streicher says.
More recently, in November 2025, the FDA removed the boxed warning that had long been on HRT menopause products. This followed the advice of an expert panel, which believed that some risks of hormone therapy had been overstated. Leading expert groups, such as The Menopause Society and the American College of Obstetricians and Gynecologists, released statements supporting this change.
For some women, progesterone isn’t the best option for a variety of reasons, including a lack of tolerance that results in moodiness, bloating, and irregular bleeding. In those cases, you can work with a healthcare professional, like a Midi clinician, to find a better dose or alternative treatment.
Read on to learn about the important role that progesterone plays in HRT, plus info on dosing and safety, as well as how a menopause-informed clinician, like one at Midi, can help you find your best options for symptom relief.
What Is the Lowest Dose of Progesterone for HRT?
First, let's address the question you came here for. At Midi, the lowest dosage of progesterone for HRT that clinicians start many women on is usually progesterone 100 mg daily. But like all menopause treatments, progesterone dosing is highly individual. It differs from person to person whether progesterone is recommended, how much to take, and in what form, so you’ll want to work with your clinician to figure out what’s best for you and your goals.
"The lowest dose of progesterone for HRT is really dependent on how much estrogen you're taking, because the purpose of the progesterone is to protect the lining of the uterus. When you use estrogen alone, you can get a buildup of that lining, which over time can increase the risk of uterine cancer," explains Dr. Streicher. "There are typical doses that people are prescribed based on standard doses of estrogen, but it's very individual. And if someone is not tolerating progesterone well, there are alternatives."
As for the higher doses? Most people peak at around 300 mg, says Midi Physician Lily Hanna, MD. More than that, “and the symptoms will start to get in the way,” she says. “A lot of folks, if they’re taking too much progesterone, feel groggy in the morning and develop brain fog.”
To get personalized recommendations based on your symptoms and health history, you can book a virtual visit with a menopause specialist through a platform like Midi.

Hormone Replacement Therapy (HRT) 101
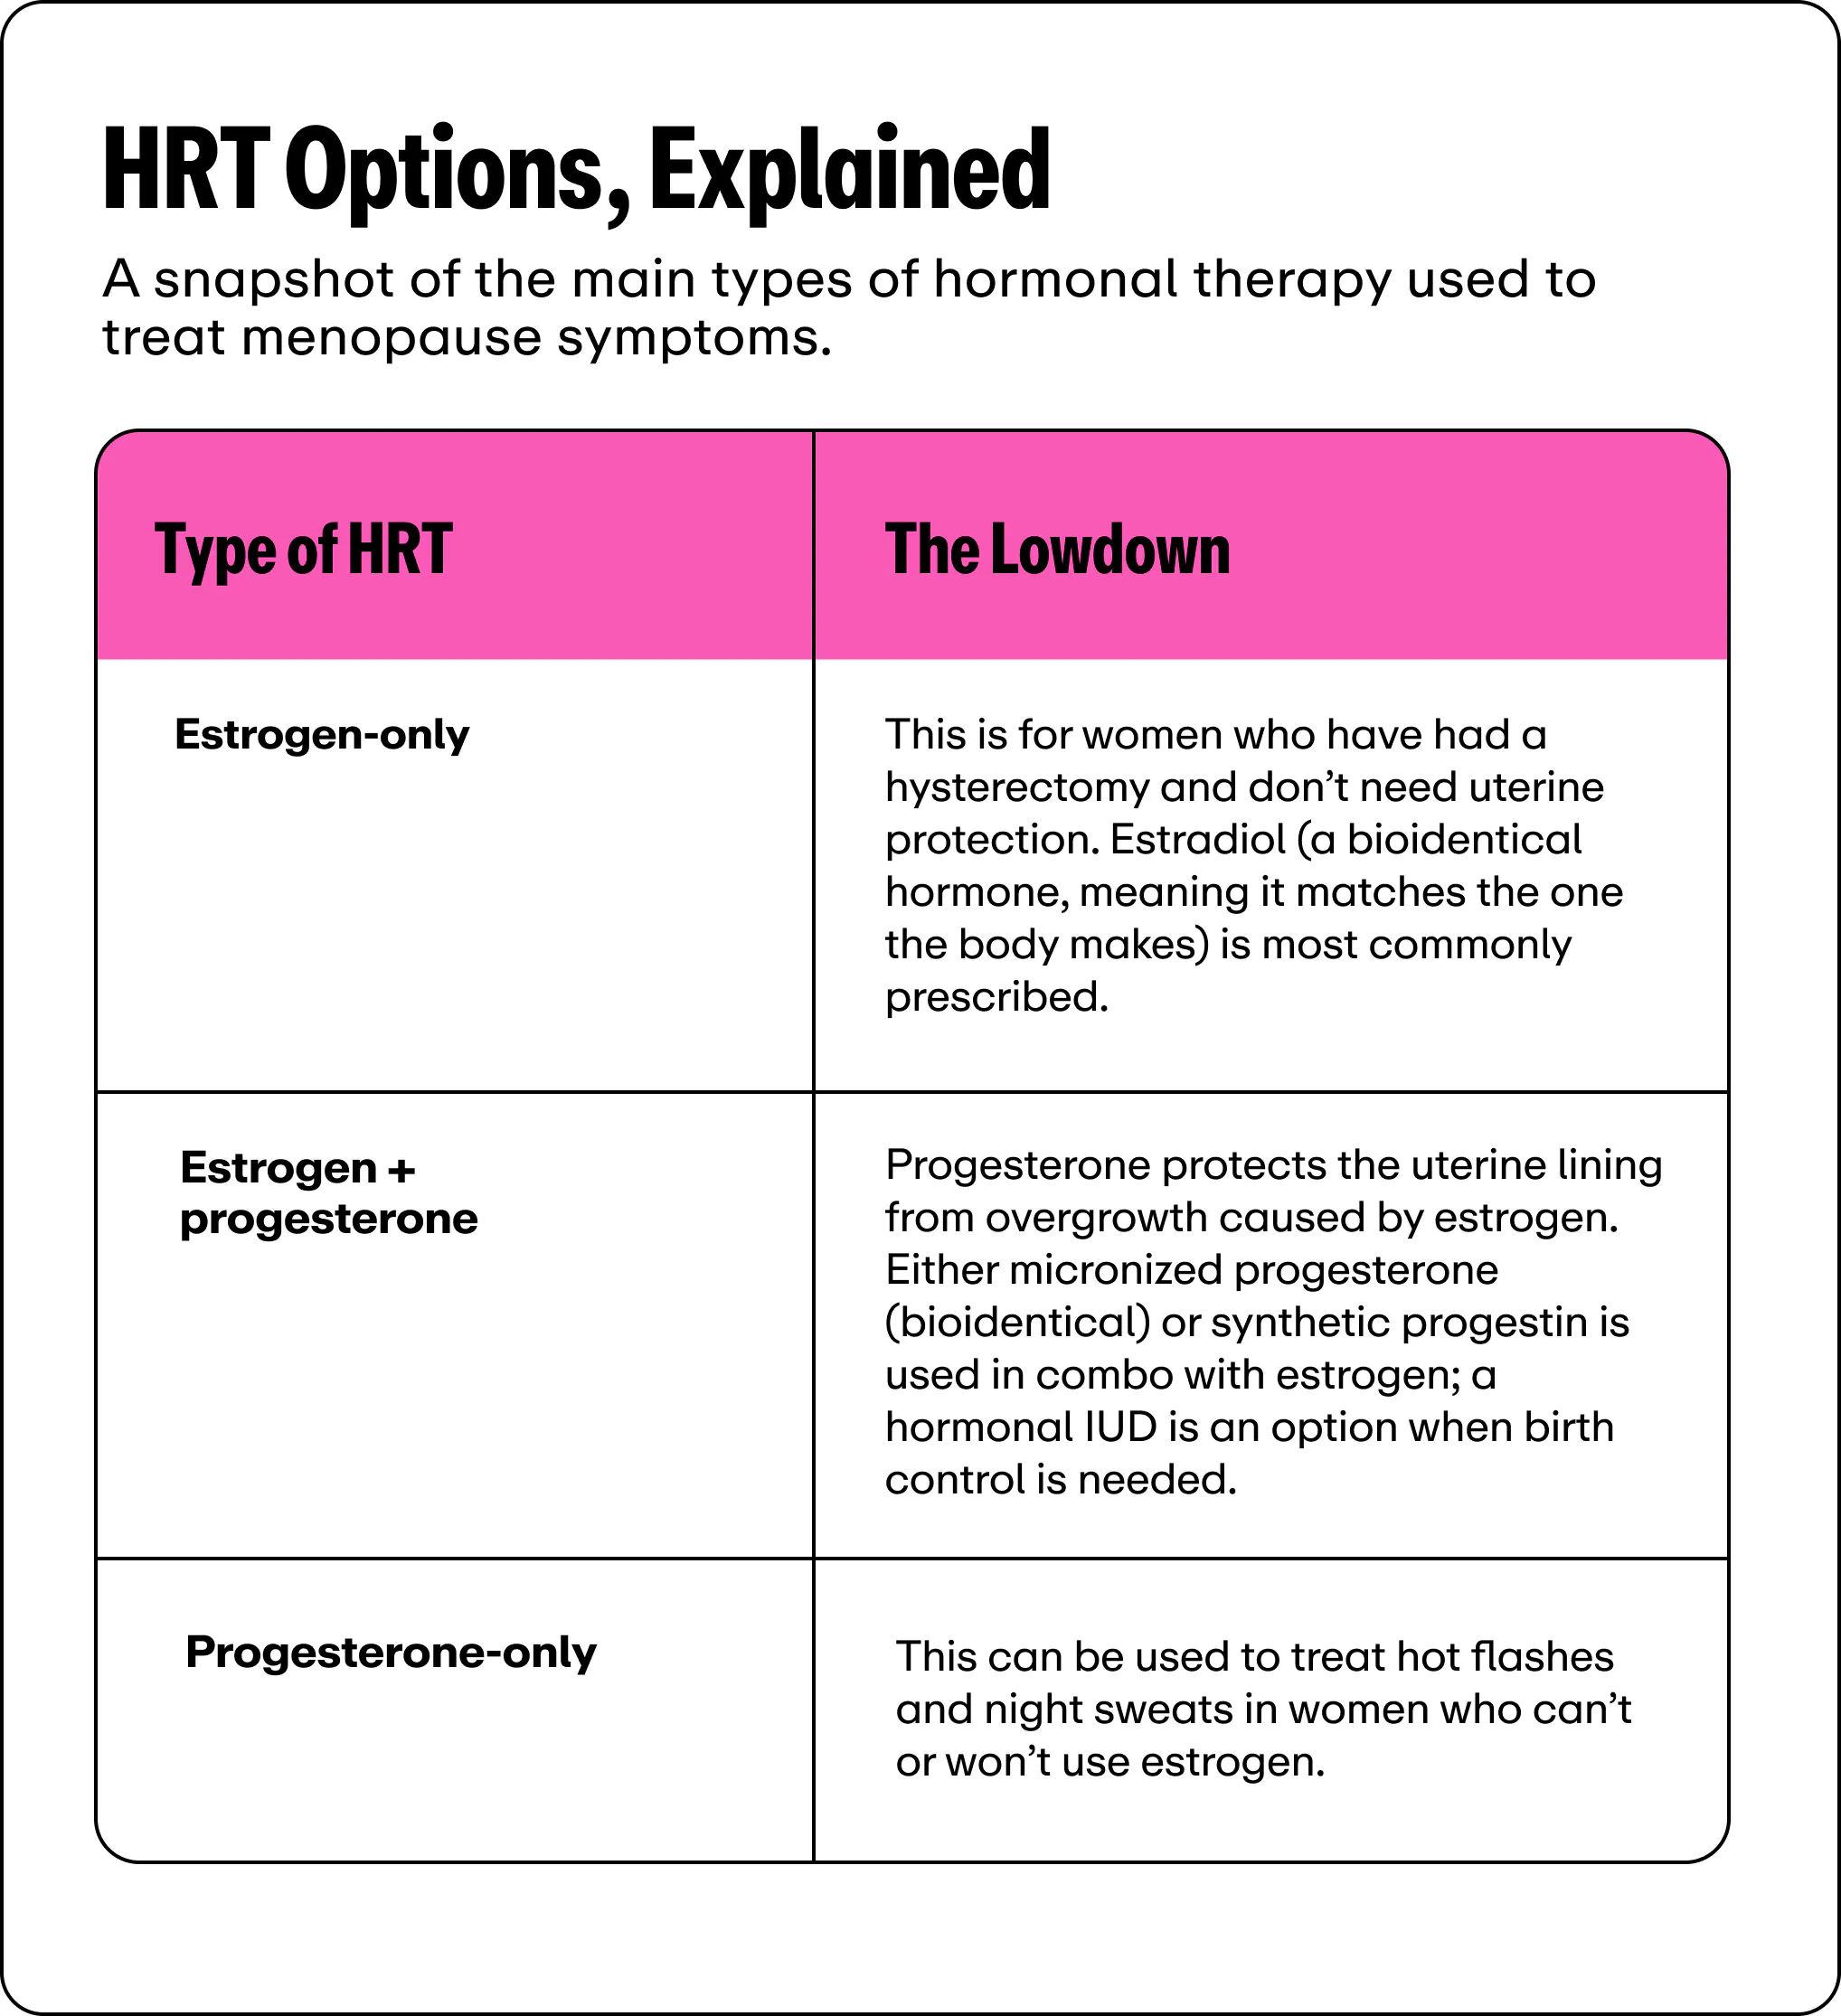
HRT is a treatment for perimenopause and menopause that replenishes hormones that naturally decline as you age. It comes in two main forms: combined estrogen and progesterone therapy (the most common form) and estrogen-only therapy.
Hormone therapy is the most effective treatment for relieving menopausal hot flashes, night sweats, vaginal dryness, and recurrent urinary tract infections (UTIs), according to the most recent guidelines from The Menopause Society. HRT may also help improve sleep issues.
Which HRT route you take depends on many factors, including your medical history. A clinician can help you determine the approach that’s best for you.
Understanding Progesterone’s Role in HRT
You might hear progesterone referred to as progestin; progestin is the synthetic (or lab-made) form of progesterone. We’ll use the term “progesterone” when we’re talking about HRT.
When it comes to HRT, progesterone serves two important purposes:
- Balances out the uterine lining: Estrogen is the MVP when it comes to relieving menopause symptoms, like hot flashes that aggravate your day, night sweats that disturb sleep, vaginal dryness that makes sex uncomfortable, or a lower libido that makes you want to swear off sex in the first place. That’s why estrogen needs to be on board in HRT. However, as effective as estrogen is for easing symptoms, taking the hormone may also thicken the uterine lining. In some cases, that lining can grow too thick, which is a risk factor for uterine cancer, a type of cancer affecting more than 890,000 women in the United States as of 2023. Adding progesterone to HRT is key because it reduces this thickening and sends the risk for developing uterine cancer back to baseline.
- Helps you sleep better: This is actually considered to be a good side effect of progesterone. About half of women have sleep problems during menopause, whether it’s trouble falling asleep, difficulty staying asleep, or getting up long before your alarm. “We know that progesterone can cause sedation and help with sleep,” says Midi’s Chief Clinical Officer Mindy Goldman, MD, a practicing OB-GYN at the University of California, San Francisco (UCSF) for almost 3 decades, who currently serves as the Director of the UCSF Gynecology Center for Cancer Survivors and At-Risk Women.
How to Know if You Need Progesterone
To determine whether progesterone is recommended for you, it helps to keep a few key factors in mind. Consider these questions when talking with your clinician:
- Do I need contraception? During perimenopause, you can still get pregnant (yes, really!), even if ovulation is becoming irregular. If you’re not looking to grow or start a family and you’re perimenopausal, your clinician will most likely suggest you take progesterone in the form of hormonal birth control. Once you’re no longer ovulating, your clinician will recommend taking it as part of HRT, depending on your symptoms.
- Am I a candidate for progesterone? If you’ve had a hysterectomy, then your clinician will suggest estrogen-only therapy. You don’t need progesterone, since there’s no risk of developing uterine cancer, but you still may benefit from some of its perks. If you still have a uterus, that’s when progesterone will most likely come into play.
- Is there any reason I should avoid progesterone? In some instances, having a peanut allergy would mean you should avoid certain types of progesterone. That’s because progesterone capsules contain peanut oil—but a peanut-free compounded progesterone may be an option. There are also many health-related reasons why you might not be a candidate for HRT in general, including having hormone receptor-positive breast cancer. A thorough chat about your health history with your clinician is important.
- How often do I need progesterone? Progesterone can be taken every day or certain days of the month (cyclically). Your clinician will go over your options and recommend the route that may help you feel your best.
Understanding Your Progesterone Dosage Options
Progesterone is available in several forms:
- Pill: Progesterone pills are the most common form prescribed to start.
- Hormone IUD: If you’re experiencing side effects on an oral progesterone pill, your clinician may recommend an IUD. An IUD is placed by your clinician, and it will provide a continuous low dose of progesterone that you don’t have to think about. (It’s truly set-it-and-forget-it.)
- Vaginal progesterone: This is another alternative, though it’s less clear how well it balances and protects your uterus, due to the lack of long-term data.
- Patch: If you have side effects from oral progesterone and don’t want an IUD, then a combination estrogen-progestin patch might be a good option for you.
The first-line recommendation is oral progesterone, prescribed in one of three ways, and the dosages can vary. The lowest dose of progesterone for HRT may work for you, but it may not. Every woman’s experience is different, which is why working with a clinician who truly understands the nuances of HRT can help you land on the most effective, safest treatment for you.
Progesterone dosage chart for menopause and HRT
The right progesterone dosage for you depends on whether your clinician recommends you take this medication continuously (every day) or cyclically (for a set number of days each month). Always defer to your clinician’s guidance, but here’s a progesterone dosage chart with what you can typically expect:
Keep in mind that your progesterone dose will scale with your estrogen dose. Also, you may see over-the-counter (OTC) progesterone creams on pharmacy shelves—these are not proven to protect the uterine lining.
Here, three common regimens on when to take progesterone for HRT:
- Daily with estrogen: In this case, progesterone is taken as a 100-mg dose nightly in the form of an oral capsule, along with an estrogen patch. This is often what Midi clinicians recommend. Why take progesterone at night? It may help you sleep better, something you obviously want every night, if possible! And with a daily regimen, there’s less of a risk of having withdrawal bleeding—in other words, bleeding that happens when you stop taking the medication and your hormone levels drop. (This is what happens on oral birth control pills during your “period” week.)
- Certain days of the month, with estrogen: An oral dose of progesterone at 100 or 200 mg, taken for 12 days each month, along with an estrogen patch, may be more suitable for some women.
- Daily, without estrogen: If you have hot flashes and night sweats that disrupt your sleep but your clinician advises against taking estrogen, there’s an option to take progesterone alone—more on this below.
Can you take progesterone every other day?
Daily doses of progesterone with estrogen are often the first-line recommendation. Some forms of progesterone may be prescribed to be taken on certain days of the month only, such as 12 to 14 days out of a 28-day cycle. On this schedule, the standard dose your clinician will probably recommend is 200 mg taken at bedtime for 12 days per month, typically days 1 to 12.
So, no—every other day is not an established treatment.
If you forget to take a dose of progesterone, you should take it as soon as you remember. But if it’s already fewer than 12 hours until your next dose, you can skip the one that you missed and take the next one at the usual time.
“Usually I'll say, just take the pill the next day when you remember it,” says Dr. Hanna.
Never take two doses at once to make up for a missed dose, and always follow your clinician’s guidance. Check in, too, if you’ve missed multiple pills: “If you skip one pill for the month, that's very different from skipping a couple of pills every week,” notes Dr. Hanna.
Is 200 mg of progesterone a high dose?
No. 200 mg is considered a standard dose of progesterone and is not abnormally high or unsafe. As part of standard cyclic hormone therapy, your clinician will likely recommend you take 200 mg of progesterone as a single dose at bedtime for 12 days within a 28-day menstrual cycle.
If you’re wondering “Is 300 mg of progesterone too much?,” that dose is sometimes prescribed as well. For instance, if you’re struggling with severe perimenopausal or menopausal insomnia, your clinician might prescribe between 200 and 300 mg of micronized progesterone to be continuously taken nightly. Clinical trials and meta-analyses have demonstrated that this dosage provides significantly greater improvements in sleep quality than lower doses.
Can You Take Progesterone Without Estrogen?
Yes, it’s definitely possible and safe to take progesterone without estrogen, known as progesterone-only therapy. Your clinician might prescribe this for a few different reasons, including if:
- You’re still experiencing hot flashes and night sweats, but you can’t take estrogen. This might be the case if you’re postmenopausal or have a history of stroke or hormone-sensitive cancers. In one 2020 review, taking oral micronized progesterone on its own helped with night sweats. Your clinician may start you with 100 mg nightly and increase it to 200 or 300 mg if needed.
- You’re in perimenopause and are having severe sleep challenges. In this case, your clinician might recommend 100 mg to 300 mg nightly micronized progesterone.
So yes, taking progesterone without estrogen is definitely an option. Just keep in mind that for managing certain menopause symptoms and protecting bone health, progesterone isn’t as effective as estrogen.
Is Progesterone Safe? What About Side Effects?
Progesterone helps protect your body from uterine cancer. Unlike oral estrogens and certain synthetic progestins, micronized progesterone has a low risk of causing blood clots, and it seems to carry a lower breast cancer risk when combined with estrogen.
That said, HRT in general might not be right for everyone. Oral estrogen slightly raises the risk of blood clots, and estrogen-progestin therapy slightly raises breast cancer risk.
But when the FDA removed the boxed warning that had previously been on HRT in November 2025, the agency pointed out that some risks of hormone therapy had been overstated. The boxed warning about endometrial cancer remains on systemic estrogen-alone products, which is exactly why women with a uterus take progesterone.
There’s good evidence that taking HRT delivers more benefits than risks if it’s within 10 years of the start of menopause or you’re younger than age 60. If you’re over age 60 or it’s been more than 10 years since your last period, it’s best to discuss your options with a clinician, like one at Midi, to find the most appropriate treatment for you.

Side effects can occur when starting progesterone, such as:
- bloating
- breast tenderness or swelling
- fatigue
- moodiness
- stomach upset
- headaches
Here’s the good news: Most of these symptoms go away on their own within 2 to 4 weeks as your body adjusts to progesterone. If you have questions about the best way to manage them, schedule a visit with a Midi clinician or other healthcare professional. And if you find that side effects aren’t tolerable or you feel worse than you did before taking progesterone, follow up with your clinician to see whether any adjustments can help.
In addition, certain severe side effects are rare but possible, such as:
- depression
- fast heart rate
- migraine
- severe dizziness or faintness
- sharp chest pain
- weakness or numbness in arms or legs
This is not a comprehensive list—reach out to your clinician or seek medical help immediately if you notice a severe side effect or have questions about any side effects after starting the medications.
Will Progesterone Affect My Weight?
Because weight gain is often linked to menopause, many women wonder whether HRT and progesterone might cause weight gain. Actually, some studies suggest that HRT that includes progesterone can help keep your weight stable and prevent excess weight gain.
Clinical trials have shown that bioidentical oral micronized progesterone doesn’t contribute to true weight gain or body composition shifts. One randomized trial found that progesterone did not change weight or waist circumference over 3 months.
When you first start taking hormone therapy, it’s normal to experience bloating, abdominal fullness, or mild fluid retention. This happens because progesterone relaxes your smooth muscle and slows digestion. This typically gets better after a few weeks.
There’s a distinct perk to HRT, because managing menopause symptoms can improve your sleep and mood. And that can make it easier to stick with habits like exercise or healthy eating, which can move the needle on the scale and help you build muscle. Medication affects everyone differently, so if you have concerns about weight gain or loss after starting progesterone, connect with your clinician.
True Stories Of Transformation
What Are Alternative Treatment Options to Progesterone and HRT?
For some women, HRT may not be the right choice. But that doesn’t mean you’re stuck with sweaty days and nights and all the other disruptive symptoms. Here are some non-hormonal options:
- Prescription options: Non-hormonal prescription options include certain antidepressants, gabapentin (ideal for night sweats and sleep), and some bladder medications. Fezolinetant and ospemifene may help vaginal dryness and painful sex.
- Hormone alternatives for uterine protection: If you’re having trouble tolerating oral progesterone, your clinician may suggest a levonorgestrel IUD, such as Mirena (this is considered the gold-standard alternative).
- Herbs and botanicals: Botanicals with some evidence for easing some symptoms include black cohosh, Siberian rhubarb, Relizen (flower pollen extract), and maca.
- Lifestyle changes: Focus on improving your sleep, eating a healthy diet, minimizing alcohol, and getting regular exercise. “These can alleviate so many symptoms,” Dr. Goldman says.
- OTC vaginal products: Vaginal lubricants and moisturizers can help with vaginal discomfort and painful sex.
Monitoring and Adjusting Progesterone Dosage: Schedule Regular Check-Ups
When you start progesterone, it’s a good idea to schedule a quick check-in with your clinician within 4 to 6 weeks, as well as a follow-up visit after 2 months to talk about how the dosage is working. You may notice some cramping, bloating, and mild moodiness, but these are expected to go away as your body adjusts to your dosage. If you’re feeling worse—not better—after adding progesterone, reach out to your clinician.
Remember: Don’t think you just have to power through uncomfortable symptoms alone—your clinician can help you find the best, most effective treatment plan for you. Sometimes lifestyle changes may help you feel even better and mitigate side effects from progesterone, so you can still enjoy its benefits.
How Much Progesterone Is Too Much?
If you’re taking oral micronized progesterone as part of hormone therapy, your clinician would rarely prescribe you more than 300 mg daily, which is within the range of standard doses. Wondering whether 400 mg of progesterone is too much? That dose would be unusual, but it might be prescribed if your clinician recommends stopping your periods for a medical reason.
There aren’t many symptoms of too much progesterone, but more than 300 mg progesterone may bring on:
- grogginess in the morning
- dizziness
- feelings of being heavily sedated
- gastrointestinal (GI) discomfort
Key Takeaways
- Progesterone is a hormone often used in hormone replacement therapy (HRT), alongside estrogen. HRT treats symptoms like hot flashes, night sweats, brain fog, and sleep issues.
- The key to taking progesterone is working closely with your clinician. You’ll start on the lowest possible dosage of progesterone for your needs, with increases if necessary. When treatment is tailored specifically to you, it’ll give you the best shot at managing the symptoms of menopause while reducing the chance of side effects.
- The lowest dosage of progesterone for HRT is usually progesterone 100 mg daily, but progesterone dosing is highly personal. Symptoms of too much progesterone HRT are unlikely but might include grogginess or dizziness.
- HRT, including progesterone specifically, is available in several forms and dosages, so your clinician can find the best option for you. Your clinician can adjust the form of progesterone and tweak the dosage. Sometimes, all you need is a small adjustment to get the right hormonal recipe for your body.
Frequently Asked Questions (FAQs)
Is 100 mg of progesterone a lot?
No, 100 mg of progesterone is standard and likely the lowest dosage of progesterone clinicians prescribe for HRT. Between 100 and 200 mg is typical and not abnormally high or unsafe.
What happens if you miss a dose of progesterone?
If you miss a dose of progesterone, take it as soon as you remember, unless it’s almost time for your next dose—in that case, skip the dose you missed, then return to your regular schedule. You shouldn’t take two doses at once. Ask your clinician if you have any questions.
How long should you take progesterone?
This depends on how long your clinician recommends staying on estrogen and hormone therapy in general—and the answer is highly personal. It’s very common to stay on hormone therapy for 2 to 5 years to manage menopause symptoms, and some women take these medications for longer.
How much progesterone cream should I use?
Progesterone cream isn't considered effective for protecting the uterus during hormone therapy, and it isn’t a substitute for prescribed progesterone when you take estrogen and have a uterus.
Do you need progesterone after a hysterectomy?
Progesterone is included with estrogen in combination hormone therapy to balance out the uterine lining. If you no longer have a uterus, you don’t need progesterone for uterine protection and can use estrogen-only hormone therapy. But some women may still want to take progesterone for sleep support.
If you’re in perimenopause or menopause and want guidance from clinicians who specialize in women’s midlife health, book a virtual visit with Midi today.
Hormonal change is at the root of dozens of symptoms women experience in the years before and after their period stops.
Our trained menopause specialists can help you connect the dots to guide you towards safe, effective solutions.
Whether you need personalized guidance or a prescription routine to tackle symptoms—including brain fog, hot flashes, sleep trouble, mood swings, and weight gain—we’ve got you covered.
Midi’s mission is to revolutionize healthcare for women at midlife, wherever they live and whatever their health story. We believe that starts with education, to help all of us understand our always-changing bodies and health needs. Our core values guide everything we do, including standards that ensure the quality and trustworthiness of our content and editorial processes. We’re committed to providing information that is up-to-date, accurate, and relies on evidence-based research and peer-reviewed journals. For more details on our editorial process, see here.


